Read the institutional account, the patient dispute and unresolved care decisions side by side. Documentation should show outcomes as well as events.
1 · The case question
The central issue is continuity: when an established treatment pathway ended, who could make the next clinical decision, what information did they use, and what workable plan existed while that decision was pending?
Matthew's case account, 6 October 2026: a recorded problem is not a completed outcome. Advocacy illustration; not a formal finding of breach.Read diagram text
Filed. Not solved.
A recorded problem is not a completed outcome.
Matthew’s case account · 6 October 2026
The next decision still needs an owner.
Advocacy illustration.
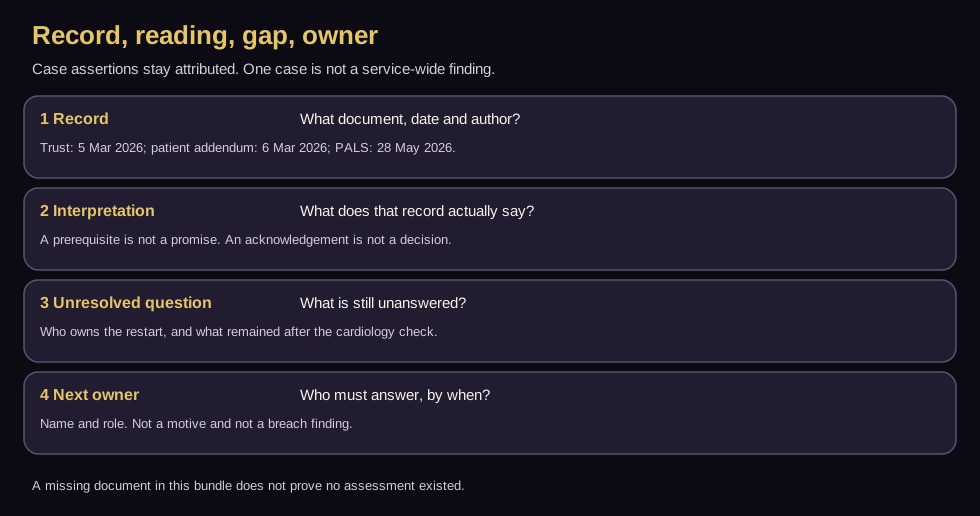
A worksheet for record, interpretation, unresolved question and next owner. Case assertions keep their source. Not a formal breach finding.Read diagram text
Columns: record; interpretation; unresolved question; next owner.
Attribution: AUTHOR-ACCOUNT trust letter 5 March 2026; AUTHOR-ACCOUNT patient addendum 6 March 2026; AUTHOR-ACCOUNT PALS correspondence 28 May 2026.
A prerequisite is not a promise. An acknowledgement is not a decision. A missing document in this bundle does not prove no assessment existed. No clinician-motive image. No formal breach finding.
2 · What the records say
CWPT's 5 March 2026 letter records a discharge request on 11 December 2025 after an offered review. It declines an interim prescription, describes reassessment and titration as necessary, and says review will follow the waiting-list pathway.
Matthew's 6 March addendum disputes the context of that discharge and the completeness of the account. He describes preceding treatment interruption, severe physical symptoms and deterioration, and argues that these risks were omitted.
The 28 May correspondence states that ADHD medication cannot be considered until full cardiology checks are completed. That is a prerequisite, not a promise that completion alone guarantees prescribing.
Discharge correspondence, contemporaneous notes and dispensing history
Restarting treatment
Individual assessment, reasons, alternatives and responsible clinician
Managing the wait
Interim clinical plan, risk assessment, review trigger and owner
Cardiology prerequisite
Requested assessment, result, interpretation and next decision
Communication and advocacy
What questions were answered, adjustments considered and advocate input recorded
4 · What an adequate explanation must distinguish
A documented refusal, its stated rationale, a disputed omission and a completed alternative plan are different facts. A record of symptoms is not itself evidence that a clinical response occurred. Equally, a missing document in this supplied bundle does not prove that no assessment ever existed.
5 · What can be generalised
Use this case to ask better continuity questions and identify possible patterns to investigate. A single case does not establish the conduct of every NHS service, a clinician's intent, a biological mechanism or a formal finding of negligence. The strongest account identifies the exact record, disputed point and unresolved decision.
6 · Sources and onward routes
Matthew's timeline carries the dated timeline. Records and escalation explains a records route; When treatment stops turns ownership questions into a request. Selected summaries are attributed to the author’s account. Private documents, identifiers and document-level linkages are not included in public site assets.
Uncertainty
Matthew's reported experience is substantive evidence of his experience. Causation, diagnosis, the appropriate restart plan and regulatory/legal conclusions require their own supporting evidence. This page has no later cardiology result or dispensing record from which to resolve those questions.
Sources cited
AUTHOR-ACCOUNT Author’s account, published with the author’s authorization (Personal account; not independently verified from public case documents)